
Medical Equipment &
Hospital Bed Insights
Explore professional guides, clinical innovations, and technical standards from Erpomed.
Healthcare Furniture
Innovations & Trends
Stay informed with expert news on ICU beds, delivery tables, and medical equipment standards.
2026 Top 4 Motor ICU Electric Hospital Bed Buying Guide
Table of Contents
- Understanding Motorized ICU Electric Hospital Bed Functions
- Evaluating Patient Safety, Clinical Features, and Adjustability
- Comparing the Top Four Motor ICU Electric Hospital Bed Types
- Checking Materials, Infection Control, and Maintenance Requirements
- Selecting the Right Bed for Your Facility and Budget
- FAQS
- Conclusion
- Related Posts
In 2026, choosing a hospital bed is a clinical and operational decision, not a simple equipment purchase. A 4 motor icu electric hospital bed can adjust the backrest, knee section, overall height, and Trendelenburg position. These movements support ventilation, patient transfers, pressure management, and safer bedside procedures. Small details matter. A quiet actuator, sealed control panel, and easy-clean surface can change a nurse’s daily workload.
The World Health Organization’s Global Patient Safety Report 2024 states that approximately one in ten patients experiences harm during healthcare, while more than half of this harm is preventable. That finding gives bed selection greater importance. Stable positioning, reliable brakes, visible angle indicators, and suitable side-rail design can reduce avoidable risks. The U.S. FDA’s hospital bed guidance also emphasizes entrapment hazards and dimensional assessment. Buyers should therefore review mattress compatibility, rail gaps, emergency lowering, and safe working loads rather than relying on motor count alone.
This 2026 buying guide compares four leading ICU electric hospital bed options through practical clinical criteria: adjustment range, patient safety, infection control, durability, and total ownership cost. It also refers to IEC 60601-2-52, which defines safety and essential performance requirements for medical beds. Certification must be verified for the destination market. Marketing claims are not evidence. Ask for test reports, warranty terms, service records, and a demonstration with a real mattress and monitor setup. Some specifications look impressive on paper but disappoint beside a crowded ICU bed. That is worth questioning.
Understanding Motorized ICU Electric Hospital Bed Functions
2026 Top 4 Motor ICU Electric Hospital Bed Buying Guide
Understanding Motorized ICU Electric Hospital Bed Functions
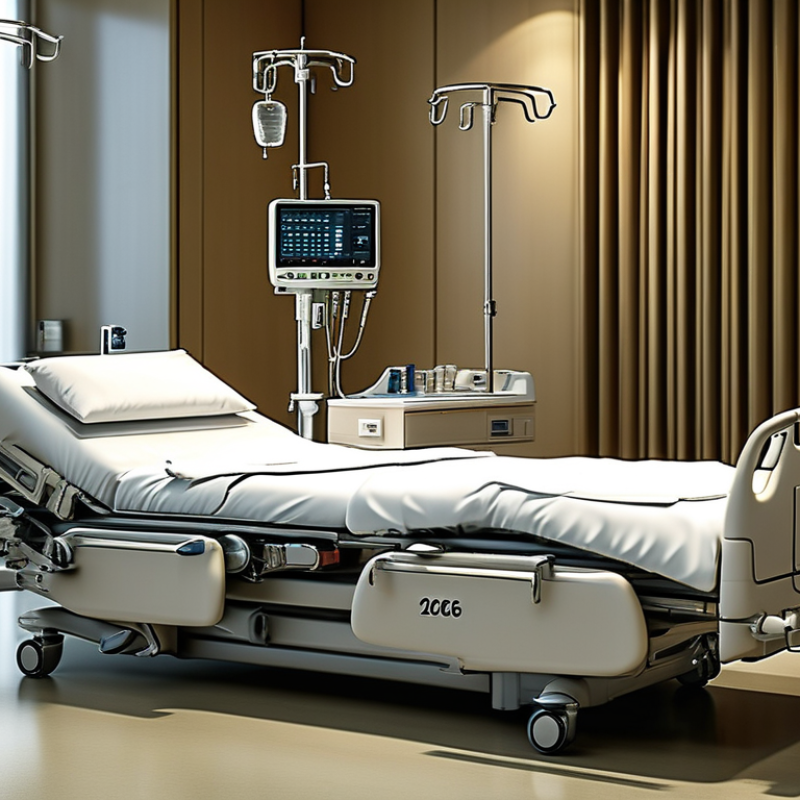
A motorized ICU bed supports safer positioning, faster care, and better patient comfort. Its functions should match real clinical routines.
The electric height adjustment helps nurses work with less bending during procedures. It also lowers the platform for safer patient transfers. Backrest and knee-rest motors create flexible positions for breathing support, feeding, and examination. Trendelenburg and reverse Trendelenburg functions assist selected clinical procedures. Use them only under trained supervision and facility protocols.
The CPR release should lower the backrest quickly during emergencies. It may be manual, electric, or both. Check its access from either side of the bed. Side rails need secure locking, smooth movement, and clear gap control. Small details matter. A patient controller should use large, recognizable buttons. Staff controls should prevent accidental operation.
Strong castors and central brakes improve movement and stability. The frame must support the patient, mattress, and equipment without exceeding its rated load. Battery backup is valuable during power loss, but its runtime varies. Test it regularly. Cleaning access also matters around joints, rails, and control panels. Fluid can collect in hidden areas.
A bed can appear advanced yet feel awkward in daily use. Clinical teams should test each function with gloves, blankets, and attached equipment. Noise, vibration, and slow motors may affect rest and workflow. Ask maintenance staff about spare parts, inspection intervals, and safety documentation. No bed is perfect. The most reliable choice is the one staff can operate correctly under pressure.
2026 Top 4 Motor ICU Electric Hospital Bed Buying Guide - Understanding Motorized ICU Electric Hospital Bed Functions
This chart ranks four essential motorized ICU bed functions by practical importance in intensive care workflows. Electric height adjustment supports safer caregiver ergonomics, backrest adjustment helps with respiratory positioning, knee adjustment improves patient stability and comfort, and Trendelenburg positioning supports emergency and clinical procedures. Scores use a practical 1–5 priority scale and are intended as a buying reference rather than a brand comparison.
Evaluating Patient Safety, Clinical Features, and Adjustability
A reliable ICU electric bed should be judged by safety, clinical control, adjustability, and serviceability. The World Health Organization’s Global Patient Safety Report 2024 states that one in ten patients experiences harm during healthcare, with more than half considered preventable. Bed design therefore matters. Select a model with a genuinely low platform, secure casters, visible brake indicators, and split safety rails that reduce entrapment risks. IEC 60601-2-52 compliance should be verified through current documentation, not assumed from sales language.
Motor performance needs clinical context. Independent back, knee, and height adjustment can support ventilation, wound care, transfers, and pressure redistribution. A stable cardiac-chair position is valuable during respiratory recovery. Yet more motors do not automatically mean better care. Controls should be intuitive, lockable, and reachable without forcing nurses to lean across the patient. Mattress compatibility, safe working load, emergency CPR release, and battery backup deserve equal attention. Small details matter.
The Agency for Healthcare Research and Quality reports approximately 700,000 to 1,000,000 inpatient falls annually in the United States. Low-height positioning, bed-exit alerts, and clear rail visibility can support fall prevention, but alarms require disciplined clinical response. A 2023 evaluation may look excellent, then fail under heavy cleaning schedules or frequent transport. Request durability records, maintenance intervals, noise data, and training evidence. Do not overlook manual override access. That omission can become expensive.
Comparing the Top Four Motor ICU Electric Hospital Bed Types
In 2026, buyers should compare functions, not motor counts alone. A three-motor bed usually controls height, backrest, and knee elevation. It suits stable ICU patients and smaller budgets. Four-motor models may add Trendelenburg positioning, supporting urgent airway or circulation care. However, layouts differ by manufacturer, so confirm each actuator’s role.
Five-motor beds often provide independent Trendelenburg and reverse Trendelenburg adjustments. They offer finer positioning during ventilation, procedures, and patient transfers. Seven-motor beds may add lateral tilt, calf adjustment, or integrated weighing functions. These features can reduce manual repositioning, but they also increase training needs and maintenance points. The World Health Organization reports that about one in ten patients experiences harm during healthcare, with more than half considered preventable. Safer bed positioning may help, but it cannot replace clinical protocols. My practical concern is simple: more motors do not automatically mean better care.
Tips: Ask for a full movement diagram, not a product label. Check the safe working load, mattress platform width, battery duration, emergency CPR release, and cleaning resistance. IEC 60601-2-52 addresses essential safety requirements for medical beds, while FDA hospital-bed guidance highlights entrapment risks around rails, mattresses, and deck gaps. Test the bed with staff wearing gloves. Tiny controls can become frustrating during emergencies. Leave room for reflection: a feature used once yearly may cost more than it delivers.
| Comparison Dimension | Standard Adult ICU Electric Bed | Low-Height ICU Electric Bed | Bariatric ICU Electric Bed | Pediatric ICU Electric Bed |
|---|---|---|---|---|
| Primary Application | General adult critical care, post-operative care, respiratory monitoring, and step-down units. | Adult critical care where fall prevention and safer patient transfers are priorities. | Critical care for patients requiring a wider sleeping surface and higher load capacity. | Critical care for infants, children, and smaller adolescents with pediatric safety requirements. |
| Typical Powered Functions in a Four-Motor Configuration | Backrest adjustment, knee/leg-rest adjustment, bed-height adjustment, and Trendelenburg/reverse Trendelenburg positioning. | Backrest adjustment, knee/leg-rest adjustment, low-to-high height adjustment, and Trendelenburg/reverse Trendelenburg positioning. | Backrest adjustment, knee/leg-rest adjustment, reinforced height adjustment, and Trendelenburg/reverse Trendelenburg positioning. | Backrest adjustment, knee/leg-rest adjustment, height adjustment, and Trendelenburg/reverse Trendelenburg positioning, subject to pediatric design limits. |
| Typical Deck Width | Approximately 90–105 cm. | Approximately 90–105 cm. | Approximately 120–140 cm. | Approximately 65–80 cm. |
| Typical Overall Length | Approximately 210–230 cm, including the headboard and footboard. | Approximately 210–230 cm, including the headboard and footboard. | Approximately 220–245 cm, depending on frame width and extension design. | Approximately 150–190 cm, depending on the age range supported. |
| Typical Patient Weight Capacity | Approximately 180–220 kg. | Approximately 150–200 kg. | Approximately 300–350 kg. | Approximately 100–150 kg, depending on the pediatric model. |
| Typical Safe Working Load | Approximately 250–300 kg, including the patient, mattress, accessories, and equipment. | Approximately 220–280 kg, including the patient, mattress, accessories, and equipment. | Approximately 400–500 kg, including the patient, mattress, accessories, and equipment. | Approximately 180–250 kg, including the patient, mattress, accessories, and equipment. |
| Typical Height Range | Approximately 40–80 cm from the floor to the mattress platform, depending on the mattress thickness. | Approximately 25–75 cm, with a lower minimum height for fall-risk reduction. | Approximately 45–85 cm to accommodate the reinforced frame and larger castors. | Approximately 35–75 cm, with height limits selected for pediatric care and staff ergonomics. |
| Backrest Adjustment | Typically up to approximately 65–70°. | Typically up to approximately 65–70°. | Typically up to approximately 60–70°, subject to frame geometry and load rating. | Typically up to approximately 60–70°, with pediatric positioning limits. |
| Knee or Leg-Rest Adjustment | Typically approximately 25–40° of powered adjustment. | Typically approximately 25–40° of powered adjustment. | Typically approximately 25–40° with reinforced joint components. | Typically approximately 20–35°, depending on the intended age group. |
| Trendelenburg and Reverse Trendelenburg | Commonly approximately 12–16° in each direction; confirm the model specification. | Commonly approximately 12–16° in each direction; the low position does not replace clinical safety checks. | Commonly approximately 10–14° in each direction because of the wider frame and higher load. | Commonly approximately 10–15° in each direction, subject to pediatric clinical protocols. |
| Side-Rail Design | Split or full-length fold-down rails with integrated control panels on many models. | Split fold-down rails are commonly used to support access while maintaining fall protection. | Extra-wide reinforced rails are required; the rail width should match the mattress and deck. | Full-length enclosed or carefully designed split rails are preferred to reduce entrapment risks. |
| Recommended Mattress Width | Approximately 85–100 cm, selected to match the deck and side rails. | Approximately 85–100 cm, selected to preserve rail clearance at the lowest height. | Approximately 110–130 cm, with bariatric pressure-redistribution support. | Approximately 60–75 cm, matched to the pediatric frame and approved rail system. |
| Castor and Mobility Requirements | Usually four medical-grade castors, commonly 125–150 mm, with central or individual locking. | Usually four medical-grade castors, commonly 125–150 mm, with stable braking and directional lock. | Larger heavy-duty castors, commonly 150–200 mm, with a reinforced chassis and dependable braking. | Medical-grade castors sized for controlled movement, with secure locking and reduced pinch hazards. |
| Emergency CPR Considerations | Look for rapid CPR release, clear emergency controls, and battery-backed positioning. | Prioritize rapid CPR release that remains accessible when the bed is at a low height. | Verify that CPR release performance is maintained at the rated safe working load. | Confirm age-appropriate emergency positioning and easy access for clinical staff. |
| Battery Backup | Commonly available; useful for transport, emergency positioning, and temporary power interruption. | Strongly recommended because low-height and emergency functions may be needed away from a wall outlet. | Strongly recommended because the larger powered frame can require reliable emergency operation. | Recommended, with battery status and controls protected from unauthorized operation. |
| Best Selection Priority | Balanced functionality, interoperability with ICU accessories, cleaning efficiency, and serviceability. | Minimum bed height, fall-risk management, staff access, and reliable emergency controls. | Verified safe working load, deck width, frame strength, mattress compatibility, and maneuverability. | Entrapment prevention, pediatric dimensions, safe rail design, cleanability, and clinical usability. |
| Standards and Verification Points | Confirm applicable medical-bed safety requirements, electrical safety documentation, EMC performance, and local regulatory approval. | Confirm low-height stability, rail safety, electrical safety, EMC performance, and local regulatory approval. | Confirm load testing, structural durability, brake performance, electrical safety, EMC performance, and local regulatory approval. | Confirm pediatric-specific safety evaluation, entrapment assessment, electrical safety, EMC performance, and local regulatory approval. |
Note: Specifications shown are typical market ranges for four-motor ICU electric hospital bed categories. Actual dimensions, load ratings, positioning angles, safety functions, and regulatory approvals vary by model and jurisdiction. Always verify the manufacturer’s current technical file and the hospital’s clinical requirements before purchase.
Checking Materials, Infection Control, and Maintenance Requirements
Material selection affects cleaning, durability, and patient safety. Choose corrosion-resistant steel, sealed polyurethane surfaces, and rounded frame edges. Avoid exposed tubing, porous padding, and deep seams around the mattress platform. A smooth finish matters. It reduces places where soil and moisture can remain.
The WHO’s 2022 Global Report on Infection Prevention and Control estimates that 7 in 100 patients in high-income countries acquire at least one healthcare-associated infection. In lower-income settings, the estimate reaches 15 in 100. These figures make infection control a purchasing issue, not just a nursing task. Ask whether the bed tolerates approved disinfectants, repeated wiping, and wet-contact cleaning. The CDC also recommends regular cleaning of high-touch surfaces, including bed rails and controls. Check those controls carefully.
Maintenance requirements deserve equal attention. Select motors with accessible inspection points, protected cables, replaceable batteries, and clear fault indicators. IEC 60601-2-52 provides safety requirements for medical beds, including mechanical and electrical risks. Request load-test records, battery-cycle guidance, and preventive-maintenance intervals. Test the brake, backrest, knee section, and emergency lowering function before acceptance. I would not trust a quiet motor alone. Noise can hide declining performance. A better inspection includes cable movement, caster locking, frame stability, and cleaning damage. Maintenance teams should record failures by bed number, date, and component. Small omissions become expensive.
Selecting the Right Bed for Your Facility and Budget
When selecting a four-motor ICU bed, begin with patient acuity, staff workflow, and available room space. A low price can hide service costs. Ask nurses to test the controls with gloves while moving a simulated patient through common positions. Check backrest, knee-break, height, and Trendelenburg movement for smooth, independent adjustment.
Measure twice. Check doorways, elevator clearance, and space beside the bed. Confirm the safe working load, mattress compatibility, brake access, and emergency lowering method. Head and foot sections should release quickly, but not detach accidentally. Review electrical protection, cleaning instructions, and local medical-device requirements with your clinical engineering team. Evidence matters more than a polished brochure.
Budget beyond the purchase price. Include installation, staff training, preventive maintenance, batteries, spare parts, and expected downtime. Request a written warranty and realistic repair response times. Compare total cost over five to eight years, not only the invoice. Some facilities overbuy features that nurses rarely use. Others save money and later regret weak casters or awkward controls. That trade-off deserves honest discussion. A short pilot in one ICU can reveal noise, cable problems, and cleaning delays before wider purchasing. Keep feedback from nurses, biomedical technicians, and infection-prevention staff. Their practical experience may challenge the original specification. Good decisions are rarely perfect; they should be documented, tested, and revised when evidence changes.
FAQS
Electric height adjustment reduces bending during procedures. It also supports safer patient transfers. Backrest and knee-rest motors create flexible clinical positions. Trendelenburg functions may assist selected procedures under trained supervision. Useful, but not automatically essential.
A low platform can reduce transfer height and fall risks. A raised platform helps staff work with less back strain. Check that the lowest position is genuinely low. Sales descriptions can be vague.
Rails should lock securely and move smoothly. Clear gap control helps reduce entrapment risks. Visibility should remain clear during routine care. Test rails with gloves.
The CPR release should lower the backrest quickly. It may operate manually, electrically, or both. Staff should reach it from either bed side. Practice matters during pressure.
Three motors commonly control height, backrest, and knee elevation. Four or five motors may add positioning options. Seven motors can include lateral tilt, calf adjustment, or weighing. More motors are not always better.
Confirm staff training and facility procedures. Check attached equipment, mattress fit, and patient stability. Use controlled movements during airway or circulation care. Do not treat it as a routine button.
Battery backup supports bed movement during power loss. Runtime varies, so test it regularly. Strong castors improve movement. Central brakes improve stability during care and transfers.
Staff should operate every function with gloves and blankets. Test controls beside attached equipment. Listen for excessive noise or vibration. Check slow motors, cleaning access, and manual overrides. A showroom test is not enough.
Request current safety documentation and applicable compliance evidence. Verify the safe working load and mattress compatibility. Ask about spare parts, inspection intervals, battery duration, and training. Maintenance details can decide reliability.
Conclusion
Choosing the right 4 motor icu electric hospital bed requires more than comparing prices. This guide explains how motorized ICU beds support patient positioning, caregiver efficiency, and clinical care through independent adjustment of the backrest, leg section, height, and overall bed angle. It also examines essential safety features, including stable locking systems, side rails, emergency functions, weight capacity, and smooth controls that help reduce patient and staff risk.
The article compares four common motor ICU electric hospital bed types according to their adjustability, intended use, mobility, and clinical flexibility. It also highlights the importance of durable materials, easy-to-clean surfaces, infection-control design, reliable maintenance access, and replacement-part availability. By reviewing clinical requirements, room conditions, patient needs, staff workflow, long-term operating costs, and available budget, healthcare facilities can select a practical bed that delivers dependable performance, improves care efficiency, and supports a safer treatment environment.

Blog Tags: